

Your doctor orders an MRI and the scan is booked, but what is prior authorization, and has anyone requested it? It is a health plan’s approval before a service, and without it a claim may be denied even when care was necessary.
The request is usually handled between the ordering provider and the plan, so most patients never see it until something goes wrong. If a request or claim has already been refused, the guide on what to do when insurance denies a claim covers the next steps.
How prior authorization works
Prior authorization is a decision by the insurer that a specific service has been reviewed before it takes place. According to a pre-authorization guide for providers, the approval comes from the health plan and confirms that a particular service has been reviewed. A doctor’s order alone does not do that.
The process runs from request to decision in three stages:
- Request. The ordering provider sends the plan the diagnosis, the planned service and supporting clinical records.
- Review. Some requests are approved automatically. A payer turnaround guide explains that requests which cannot be auto-approved need clinical reviewer time. This stage is often called utilization review, and the reviewer checks the request against the plan’s medical necessity criteria.
- Decision. The plan approves, denies, or asks for more information.
Review effort is not spread evenly. The same guide says manual review concentrates in high-cost, low-volume categories such as advanced imaging, specialty drugs and inpatient authorizations. That is why a routine visit rarely needs approval while a scan or an infusion often does.
Common misunderstandings at a glance
Three assumptions cause most surprises. Each looks reasonable, and each can lead to an unexpected bill.
| Assumption | What is supported | Planning use |
|---|---|---|
| A referral is the same as an authorization | A referral usually comes from a primary care provider and directs the patient to a specialist. An authorization comes from the health plan and confirms a specific service has been reviewed. Some plans require both. | Ask the plan whether a visit to a specialist needs only a referral or also an approval. |
| Approval means the plan will pay | Authorization does not automatically mean the bill gets covered. | Treat approval as one step. Benefits and cost sharing still apply to the claim. |
| Approval can be arranged after the care | Payers allow retroactive authorization only in limited situations, such as an emergency or an eligibility error. | Confirm approval before a scheduled service rather than counting on a retroactive fix. |
These points come from the pre-authorization guide cited above.
The referral distinction matters most for people in plans that route care through a primary care provider. A referral gets the patient in the specialist’s door. It does not tell the patient that the plan has approved the specialist’s tests or procedures.
Who files the request
In most cases the ordering provider files the request, not the patient. The payer guide notes that requests needing additional information trigger back-and-forth exchanges with the ordering provider. The patient is not part of that exchange, so the office holds the paperwork and the plan’s questions.

That does not make the patient a bystander. Three habits help:

- Ask before scheduling. When a test, procedure or infusion is ordered, ask the office whether the plan requires approval and whether it has been requested.
- Expect a busy office. The guide reports an AMA survey in which practices completed an average of 39 prior authorization requests per physician each week. Physicians and staff spent about 13 hours a week on them. A polite follow-up is reasonable, and a single request can wait in a large queue.
- Keep the details. Note the service, the date of the request and who at the office is handling it, so any later conversation with the plan is specific.
How long a decision takes
Under the CMS rule known as CMS-0057-F, impacted payers must decide within 72 hours for expedited requests and seven calendar days for standard requests, as the turnaround guide describes. Expedited means urgent. Standard means non-urgent.
Actual speed can be quicker than the limit. The same guide reports a median response time of about 1 day (0.9 days) for standard requests in Medicare Advantage, Medicaid managed care and the ACA Marketplace. A median describes the typical case, so a request that needs a clinical reviewer or more records can take longer.
The federal timeframes have a defined scope. The pre-authorization guide says the rule applies to Medicare Advantage organizations, certain Medicaid and CHIP programs, and qualified health plans on the federally facilitated exchanges. It does not cover every commercial health plan, and its main prior authorization provisions exclude drugs.
Delays remain a real cost. The guide cites the AMA 2024 physician survey, in which 93% of physicians reported care delays tied to prior authorization. A patient with a scheduled procedure should ask for the request early and tell the office if symptoms worsen, because the urgent track exists for situations where waiting would be harmful.
Imaging and MRI approvals
An MRI often needs prior authorization, but not always. The guide lists MRI, CT and PET scans among the services that often require preauthorization, along with inpatient admissions, surgeries, and specialty medications with injections. It also says one plan may require authorization for an MRI while another plan may not. Requirements vary by plan, even within a single insurer.
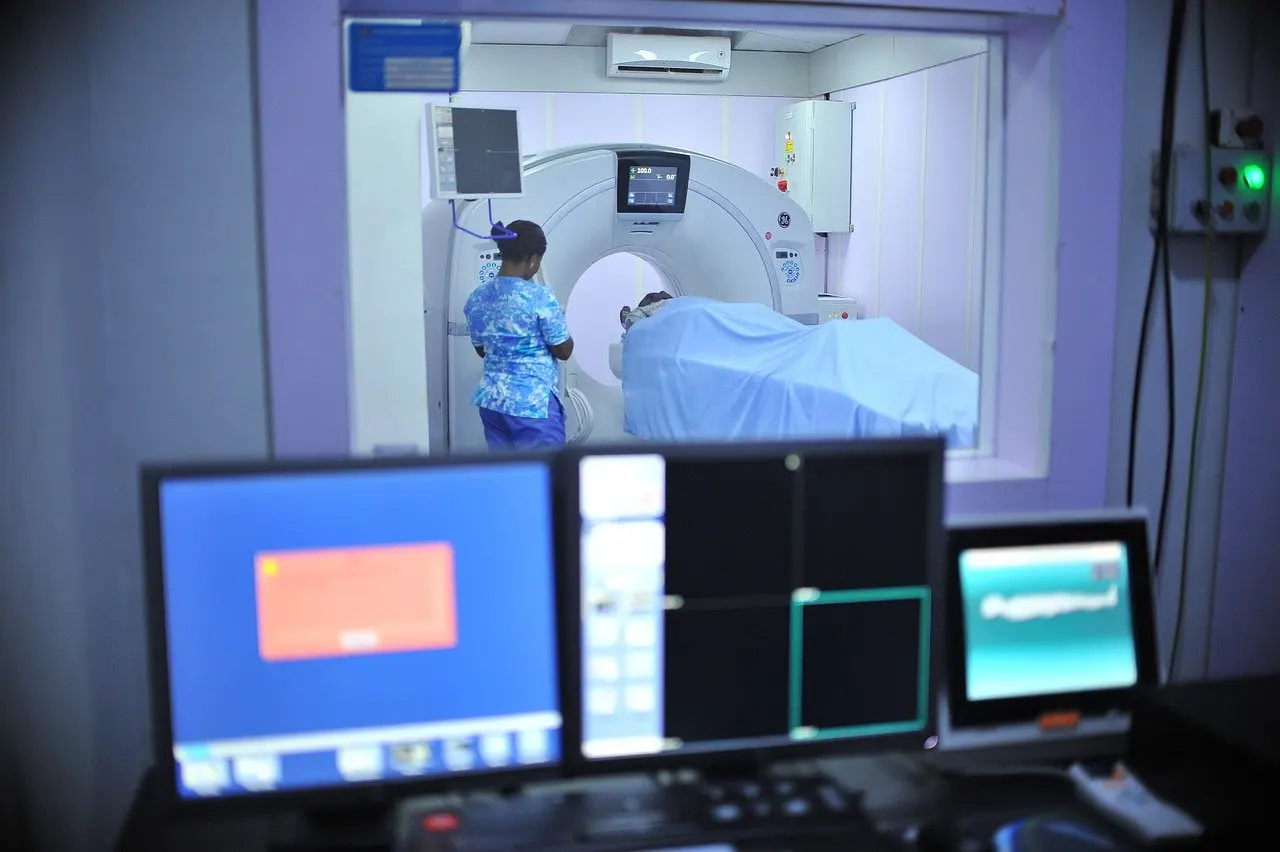
The practical reading is that the answer sits in the patient’s own plan, not in a general rule. Advanced imaging is a high-cost category where the payer guide says manual review concentrates, so it is sensible to assume a check is needed until the plan or the ordering office says otherwise. Ask the office to confirm approval before the appointment, not after the scan.
Medication approvals, formularies and step therapy
For drugs, prior authorization is tied to the plan’s formulary, which is its list of covered medications. Specialty medications are among the services the guide says often need authorization. A prescription can be written and still stall at the pharmacy counter until the plan approves it.

Step therapy is a common condition attached to drug approval. It means the patient has to try a cheaper or preferred treatment first. The guide adds that a physician can still request an exception if the required therapy is unsafe. If a medication is held up, ask the prescriber whether step therapy applies and whether an exception request fits the situation.
The federal timeframes above should not be assumed for medication, since the rule’s main provisions exclude drugs. The plan’s own drug-coverage documents are the place to look for its timing.
Care without approval
Receiving a service that required approval, without having it, exposes the patient to a denied claim. The guide states that the payer may deny the claim even when the service was medically necessary. Medical necessity and authorization are separate tests, and a service can pass the first and still fail the second.
The payer guide offers one more point worth knowing. A significant share of initial denials trace to missing documentation, not to disagreements on medical necessity. A denial after a missed approval is therefore not always a judgement about the care itself.
If a denial arrives, the order of work is simple. Find the stated reason, ask the provider’s office whether the request was filed and what it contained, and then decide whether to appeal or dispute. The article on why do health insurance companies deny claims explains the common causes. If the result is a bill, how to dispute a medical bill walks through the dispute itself.
Frequently asked questions
| Question | Answer |
|---|---|
| Is pre-authorization different from prior authorization? | For most billing situations the two terms mean the same thing, according to the pre-authorization guide. |
| What slows a request down? | Requests that cannot be auto-approved need clinical reviewer time, and requests missing information trigger exchanges with the ordering provider, per the payer turnaround guide. |
| When do the CMS-0057-F requirements start? | Several operational requirements took effect on January 1, 2026. Most API requirements begin January 1, 2027, as the guide describes. |
| Do appeals of denied requests ever succeed? | Often. The turnaround guide reports that the share of initially denied standard requests overturned on appeal was 67% for Medicare Advantage, 47% for Medicaid managed care and 43% in the ACA Marketplace. |